
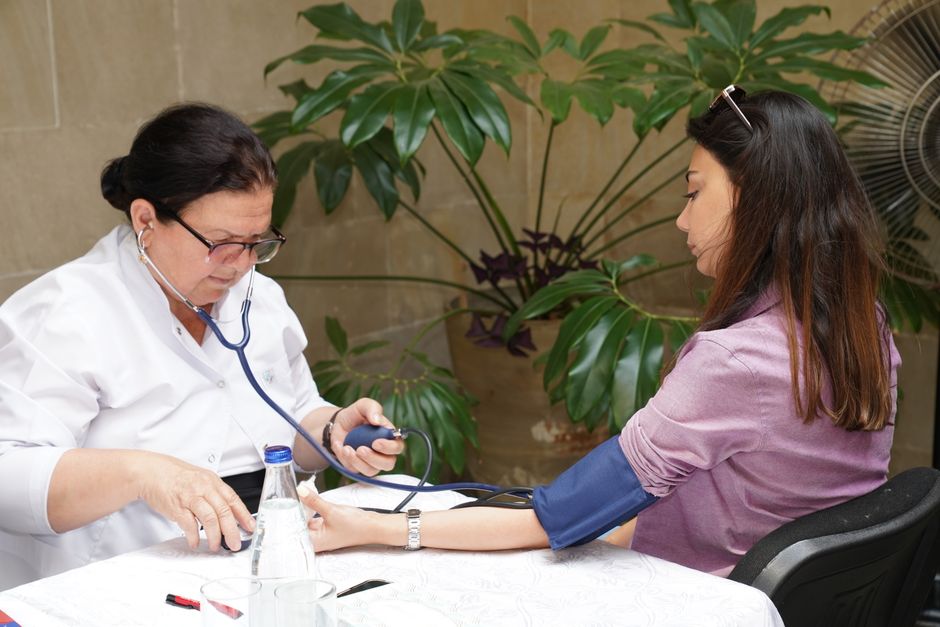
Someone needs a blood transfusion when their blood can no longer do one of its core jobs: carry enough oxygen, clot properly, or maintain enough blood volume to keep organs supplied. Transfusions are given for severe blood loss, for anemia that threatens how well tissues get oxygen, and for serious clotting problems. They are also used during some surgeries and cancer treatments. Blood transfusion is a supportive treatment, meaning it replaces something the body is missing rather than fixing the underlying cause.
Why Would Someone Need a Blood Transfusion?
A transfusion restores a specific component of blood that the body cannot replace fast enough on its own. That is the organizing principle behind every transfusion. Clinicians do not transfuse “blood” as a general tonic. They transfuse red cells, platelets, or plasma, and each one solves a different problem.
Red blood cells carry oxygen. When the red cell count or the hemoglobin inside them drops low enough, the heart and other organs may not get enough oxygen. Platelets and plasma proteins control bleeding. When they are too low or not working, bleeding becomes hard to stop. Massive blood loss creates a third problem: the body loses volume, and blood pressure can fall to dangerous levels.
A key point that surprises many people: transfusion decisions are not based on a single lab number. Doctors weigh the number against the person’s symptoms, their rate of change, and their overall health. A person with chronic anemia can function at a hemoglobin level that would cause serious symptoms in someone who lost blood suddenly.
What Conditions and Situations Lead to a Transfusion?
Most transfusions fall into a handful of recognizable categories. Knowing them helps explain why one person gets blood and another with a similar lab result does not.
- Major blood loss. Severe injuries, internal bleeding, and complicated childbirth can drain blood faster than the body can compensate. In these situations, red cells, plasma, and platelets may all be needed.
- Severe anemia. This can come from many causes: heavy menstrual bleeding, bleeding in the digestive tract, kidney disease, cancer and its treatments, or bone marrow disorders that slow red cell production.
- Chemotherapy and stem cell transplant. These treatments suppress the bone marrow, which makes red cells and platelets. Counts often fall for a period, and transfusions support the person until the marrow recovers.
- Major surgery. Some operations, such as certain heart, orthopedic, and transplant procedures, carry a meaningful risk of blood loss. Blood may be prepared in advance.
- Clotting failure. Liver disease, massive bleeding, and some medications can impair clotting. Plasma or platelets may be given when there is active bleeding or a procedure is planned.
- Certain inherited blood disorders. Conditions such as sickle cell disease and thalassemia can require transfusions, sometimes on a regular schedule, to prevent complications.
Newborns and premature infants sometimes need transfusions too, for anemia or bleeding problems. This is a specialized area with its own guidelines and is managed by neonatal specialists.
When Is a Transfusion Actually Needed? How Doctors Decide
Doctors decide using symptoms plus lab values plus the clinical picture. Hemoglobin, the protein in red cells that carries oxygen, is the most common number used. Normal hemoglobin is roughly 13.5 to 17.5 grams per deciliter for men and 12.0 to 15.5 for women, though reference ranges vary slightly by lab.
For most stable hospitalized adults, clinicians generally use a restrictive approach, giving red cells when hemoglobin falls to around 7 to 8 grams per deciliter, depending on the situation. This threshold is supported by a large body of trial evidence and is widely reflected in clinical guidance. It replaced older, more liberal practices. The shift matters because transfusions carry real risks, so avoiding unnecessary ones is safer.
The threshold is not universal. A person with active heart disease and chest pain may be transfused at a higher number. Someone losing blood rapidly needs treatment based on their stability, not a lab result that may lag behind the actual loss. And a person with chronic anemia may need transfusion for symptoms such as severe shortness of breath or fatigue that limits daily function, even at a level above the usual trigger.
For platelets and plasma, the decision depends on the count, whether there is active bleeding, and whether a procedure is planned. These thresholds are more individualized than the red cell threshold.
What Are the Different Types of Transfusion?
Blood is separated into components so each patient gets only what they need. This is more efficient and reduces exposure to parts of blood the person does not require.
| Component | What It Contains | What It Treats |
|---|---|---|
| Red blood cells | Concentrated red cells | Anemia and oxygen-carrying shortfall |
| Platelets | Clotting cells | Low platelets or platelet malfunction with bleeding risk |
| Plasma | Clotting proteins and other plasma contents | Clotting factor deficiencies and massive bleeding |
| Whole blood | All components together | Massive trauma bleeding in some settings |
Before transfusion, blood is matched to the recipient. The ABO and Rh systems are the main compatibility groups. Crossmatching tests check that the donor blood is compatible with the patient’s blood, which lowers the risk of a serious reaction. This matching process is why blood type matters so much in emergencies.
What Happens During and After a Transfusion?
A transfusion is usually given through an intravenous line in the arm. A unit of red cells typically takes one to a few hours to infuse. Nurses check vital signs before, during, and after, and watch for reactions. Most people feel nothing unusual during the process.
Mild reactions can occur. Fever, chills, a rash, or itching are the more common ones and are usually manageable. Serious reactions are uncommon but possible, including allergic reactions, lung injury, and hemolytic reactions when blood is mismatched. Transfusion-related acute lung injury is a recognized but infrequent complication that affects breathing.
There is also a longer-term consideration. Repeated transfusions can lead to iron overload, because red cells contain iron and the body has limited ways to remove excess. This matters most for people on regular transfusion schedules, such as those with thalassemia. Iron monitoring and, in some cases, iron-removal treatment are part of long-term care.
Infectious risk is now very low in countries with modern screening, though not zero. Blood is tested for major viruses including HIV, hepatitis B and C, and others. The residual risk is small but has not been eliminated entirely, which is one reason transfusions are reserved for situations where the benefit clearly outweighs the risk.
Are There Alternatives to Blood Transfusion?
Sometimes. A field called patient blood management aims to reduce or avoid transfusions where possible. It includes treating anemia before planned surgery, using medications or techniques to limit blood loss during operations, and recycling the patient’s own blood in some surgical settings.
Iron supplements and, in some cases, iron given intravenously can correct iron-deficiency anemia over time. Erythropoiesis-stimulating agents, which prompt the body to make more red cells, are used in certain situations such as kidney disease and some cancer care, though their use is limited by safety concerns and specific indications. These approaches work slowly and are not a substitute for transfusion in an emergency or when oxygen delivery is critically low.
Some people decline transfusions for religious or personal reasons. Hospitals can sometimes accommodate this with blood-sparing strategies, but the options depend heavily on the situation. In severe acute blood loss, no medication replaces blood fast enough. That is an honest limit worth stating plainly.
Why Blood Donation Matters
Every transfusion depends on donated blood. Red cells can be stored for a limited time, platelets for only days, which means supply requires steady donation. Shortages occur, and they affect which patients can be treated and how quickly.
Donated blood is screened, typed, and processed before use. The system that moves blood from donor to patient is one of the more carefully regulated parts of medicine, and it depends on people showing up to give.
Frequently Asked Questions
How low does hemoglobin have to be for a blood transfusion?
For most stable adults, clinicians generally transfuse red cells when hemoglobin falls to around 7 to 8 grams per deciliter. The exact trigger depends on symptoms, heart health, and how fast the level dropped.
Can you survive without a blood transfusion?
Many people can, depending on the cause and severity of their blood problem. In severe acute blood loss or critically low oxygen delivery, though, transfusion can be life-saving and no medication works fast enough to replace it.
How long does a blood transfusion take?
A unit of red blood cells usually takes one to a few hours to infuse. Platelets and plasma are typically given faster, and the care team monitors vital signs throughout.
What are the risks of a blood transfusion?
Common reactions include fever, chills, and rash, while serious reactions such as lung injury or hemolytic reactions are uncommon. Infectious risk is very low with modern screening but not zero, and repeated transfusions can cause iron buildup over time.
