
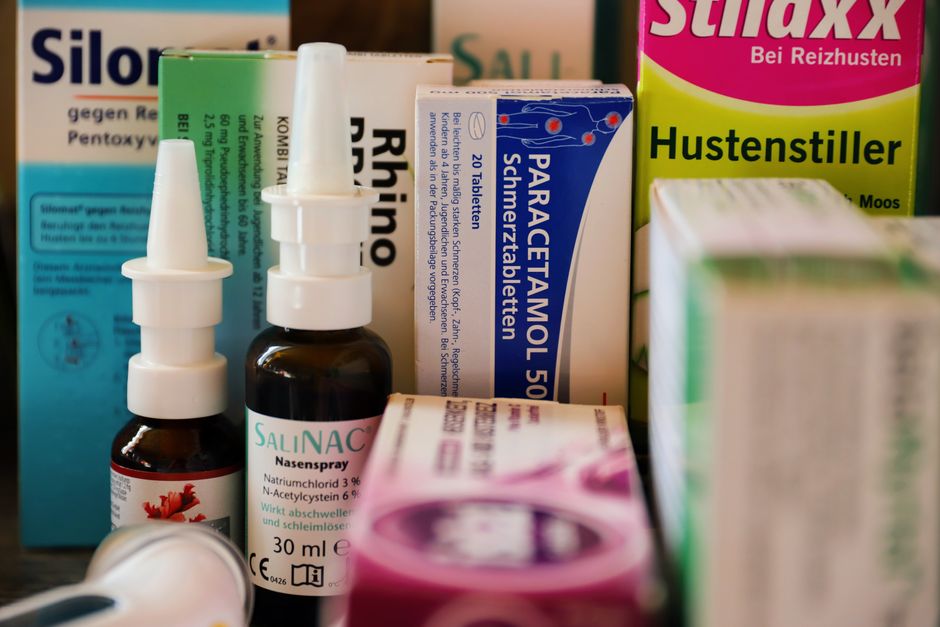
A nasal decongestant shrinks the swollen tissue lining your nasal passages so air can move through more freely. Most work by stimulating alpha-adrenergic receptors on the blood vessels in your nose, which causes those vessels to narrow. Less blood in the tissue means less swelling, and less swelling means easier breathing.
That is the short answer. The longer answer involves which drugs actually do this, how they differ, what they can and cannot fix, and why the pills you swallow work differently from the sprays you squirt. It also involves a regulatory change that surprised a lot of people who had used these products for years.
What Does A Nasal Decongestant Do to the Tissue Inside Your Nose?
It constricts blood vessels. The lining of your nose is packed with a dense network of tiny blood vessels, and when you have a cold or allergies, those vessels dilate and leak fluid. The tissue swells, the airway narrows, and you feel stuffed up.
Decongestants reverse part of that process. The active ingredient binds to alpha-adrenergic receptors on the vessel walls, the vessels tighten, blood flow to the lining drops, and the swelling goes down. This is a mechanical effect, not an immune one. The drug does not fight the virus, block histamine, or thin mucus. It changes the diameter of blood vessels.
That distinction matters. A decongestant can make it easier to breathe through your nose while doing nothing about the underlying cause of the congestion. If you have a viral cold, the infection runs its course regardless. If you have allergies, the allergen is still there.
What Is the Difference Between Oral and Spray Decongestants?
They use the same basic mechanism but deliver it very differently. Oral decongestants go through your whole body. Sprays act mostly where you put them.
Pseudoephedrine is the main oral decongestant available in the United States. It is kept behind the pharmacy counter because it can be converted into methamphetamine, and federal law limits how much you can buy at once. It works, and the evidence for its effect on nasal airway resistance is reasonably established. But because it travels through the bloodstream, it can raise blood pressure and heart rate, cause insomnia, and produce a jittery feeling in some people.
Phenylephrine is the other oral option. Here is where the story gets interesting, and it is worth understanding clearly.
In September 2023, an advisory panel to the US Food and Drug Administration concluded that oral phenylephrine at standard doses is not effective as a nasal decongestant. The problem is not that phenylephrine is a useless molecule. It is that when you swallow it, most of it is broken down in the gut and liver before it reaches the bloodstream in meaningful amounts. The FDA subsequently proposed removing oral phenylephrine from the market as a decongestant, and that process has been moving forward. Nasal spray forms of phenylephrine were not part of that conclusion, because sprayed directly onto nasal tissue, the drug reaches the target.
This is a genuinely useful clarification: oral phenylephrine and phenylephrine spray are not the same thing, even though the label ingredient looks identical. The route of delivery changes everything.
What About Decongestant Sprays and Rebound Congestion?
Sprays work fast and act locally, which limits whole-body side effects. Oxymetazoline and phenylephrine are common spray ingredients. For short-term relief of congestion, they are effective.
The catch is rebound congestion. If you use an oxymetazoline spray for more than a few days in a row, the nasal tissue becomes dependent on it. When the drug wears off, the vessels dilate more than they did before, and you feel more congested than you started. So you use more spray. This cycle has a name — rhinitis medicamentosa — and it can be hard to break.
Standard guidance is to limit oxymetazoline spray use to three days. That is a well-established limit, not a conservative guess. If you find yourself reaching for the spray every day for weeks, that is worth discussing with a pharmacist or clinician rather than continuing.




Do Nasal Decongestants Treat Allergies or Just the Stuffiness?
They treat the stuffiness. That is the whole job.
Allergies involve histamine and other inflammatory chemicals released when you encounter pollen, dust mites, pet dander, or mold. Antihistamines block histamine. Intranasal corticosteroid sprays reduce allergic inflammation over days to weeks. Decongestants do neither of those things. They shrink vessels.
So a decongestant can be a reasonable add-on when allergy congestion is severe and you need relief today, but it is not a treatment for the allergy itself. If your symptoms are seasonal and predictable, an intranasal steroid spray used consistently is generally considered more effective for controlling allergic nasal symptoms than repeated decongestant use. That is a comparison supported by clinical evidence, not just a preference.
Who Should Be Careful With Oral Decongestants?
Oral pseudoephedrine raises blood pressure in some people. For anyone with uncontrolled hypertension, heart disease, or an irregular heartbeat, that is a real concern and a reason to talk to a clinician before using it. It can also interact with monoamine oxidase inhibitors, a class of antidepressants, and that combination is considered dangerous.
Other groups where caution applies:
- People with an enlarged prostate, because the drug can make urination harder
- People with glaucoma, particularly narrow-angle glaucoma
- People with thyroid disease or diabetes, where stimulant effects may matter
- Pregnant and breastfeeding women — check with a clinician rather than deciding alone
For children, the picture is different again. Decongestants are not generally recommended for young children, and dosing guidance for infants and toddlers is limited. No clinical guidelines support routine decongestant use in very young children. If a child is congested, saline drops and suction are the usual first steps, and a pediatrician should guide anything beyond that.
What Do Nasal Decongestants Not Do?
They do not shorten a cold. They do not kill viruses or bacteria. They do not reduce mucus production, and in fact drying out the nasal lining is one reason some people find them uncomfortable with prolonged use. They do not replace saline irrigation, which physically rinses out mucus and irritants and has a good safety profile.
They also do not work instantly when swallowed. Oral decongestants take roughly 15 to 30 minutes to begin working, and the effect lasts several hours depending on the product. Sprays act within minutes.
One practical point people often miss: combination cold products frequently contain a decongestant plus acetaminophen or another pain reliever. If you take a decongestant on its own and also take a separate cold medicine, you can accidentally double up on ingredients. Reading the full drug facts label on each product is worth the thirty seconds.
When Is a Decongestant the Wrong Tool?
Congestion is not always simple. If it lasts for weeks, is one-sided, comes with facial pain, bloody discharge, or vision changes, those are reasons to see a clinician rather than manage it with over-the-counter products. Structural problems like a deviated septum, nasal polyps, or chronic sinusitis produce congestion that decongestants may ease briefly but cannot resolve.
For ordinary short-term congestion from a cold, a decongestant is a reasonable tool for comfort. It is not a treatment for the cause, and it is not meant for long-term daily use. Knowing which category you are in is the difference between using the drug well and using it in a way that creates a new problem.
Frequently Asked Questions
How long does a nasal decongestant take to work?
Sprays typically act within minutes, while oral decongestants generally take about 15 to 30 minutes to begin working. The effect usually lasts several hours depending on the specific product.
Is oral phenylephrine still effective as a decongestant?
An FDA advisory panel concluded in 2023 that oral phenylephrine at standard doses does not work as a decongestant, and the agency has been moving to remove it from that use. The nasal spray form was not part of that conclusion.
Can I use a decongestant spray every day?
No. Oxymetazoline spray should be limited to about three days of use, because longer use can cause rebound congestion that makes stuffiness worse when the spray wears off.
Do decongestants help with allergy symptoms?
They relieve the stuffiness that allergies cause but do not treat the allergic reaction itself. Intranasal steroid sprays and antihistamines address the underlying inflammation that decongestants leave untouched.
