
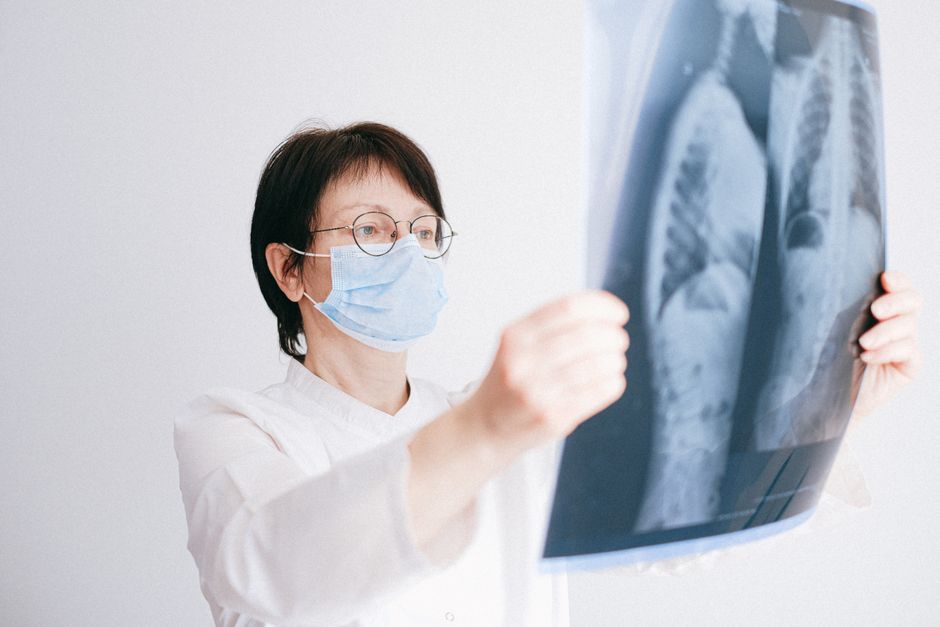
A lung capacity test measures how much air your lungs can hold and how quickly you can move that air in and out. The most common version is called spirometry, a breathing test that takes only a few minutes and involves blowing hard into a mouthpiece connected to a machine. The results help doctors detect conditions like asthma, COPD, and restrictive lung diseases, and they can also track how well a treatment is working over time.
What Is a Lung Capacity Test and How Does It Work?
A lung capacity test is a broad term for several breathing tests that measure lung function. Spirometry is the most widely used. You sit upright, place a clip on your nose so air only moves through your mouth, and breathe through a mouthpiece attached to a spirometer.
The test usually has three parts. First, you breathe normally for a few breaths. Then you take the deepest breath you can and blast the air out as hard and fast as possible until your lungs feel empty. You repeat this at least three times so the machine can pick your best effort. The whole thing takes about 10 to 15 minutes.
The spirometer records two main numbers. Forced vital capacity (FVC) is the total amount of air you can blow out after a full breath in. Forced expiratory volume in one second (FEV1) is how much air you can force out in that first second. The ratio between them — FEV1 divided by FVC — helps doctors tell the difference between obstructive and restrictive lung problems.
Obstructive conditions like asthma and COPD make it hard to push air out quickly, so FEV1 drops while FVC may stay closer to normal. Restrictive conditions like pulmonary fibrosis or chest wall disorders limit how much air the lungs can hold in the first place, so both FVC and FEV1 tend to be lower together.
Your results are compared to predicted values based on your age, height, sex, and ethnicity. A number alone means little without that context. Someone with small lungs who is healthy may have a lower FVC than a taller person with mild disease.
Why Would a Doctor Order a Lung Capacity Test?
Doctors order lung capacity tests for several reasons. The most common is to figure out why someone has ongoing breathing symptoms — shortness of breath, wheezing, a chronic cough, or chest tightness that does not have an obvious cause.
They are also used to diagnose and monitor specific conditions:
- Asthma — to confirm the diagnosis and see how well the airways respond to a bronchodilator
- COPD — to confirm airflow obstruction and grade its severity
- Restrictive lung diseases — such as pulmonary fibrosis or sarcoidosis
- Pre-surgical evaluation — to assess whether someone’s lungs can handle surgery, especially chest or abdominal surgery
- Occupational monitoring — for workers exposed to dust, fumes, or other lung irritants
- Medication monitoring — some drugs can affect lung function, and periodic testing tracks changes
Sometimes the test is part of a routine evaluation even when symptoms are mild. Other times it is used to measure whether a treatment is helping. If your FEV1 improves after using an inhaler during the test, that tells your doctor the airway narrowing is at least partly reversible — a useful clue when deciding on treatment.
How Should You Prepare for a Lung Capacity Test?
Preparation is straightforward but matters for accuracy. Your doctor will give you specific instructions, but here are the general points.
Tell your doctor about all medications you take, especially inhalers, because some may need to be held before the test. Do not stop any prescribed medication on your own without being told to. The timing depends on which drug it is and why the test is being done.
Avoid smoking for at least a few hours before the test — ideally longer. Smoking temporarily narrows the airways and can make your results look worse than they actually are. Avoid a heavy meal right before, since a full stomach makes it harder to take deep breaths. Loose, comfortable clothing helps you breathe freely.
If you have had a recent heart attack, collapsed lung, or certain types of chest surgery, the test may need to be postponed. Your doctor will make that call.
During the test, give it your full effort. The results depend on how hard and how completely you blow. Half-hearted attempts produce numbers that do not reflect your real lung function, which can lead to unnecessary tests or missed diagnoses.




What Do the Results Mean?
Results are reported as percentages of predicted values. A common way doctors describe severity is based on FEV1 as a percentage of what is predicted for someone of your age, height, and sex.
Roughly speaking:
- 80% or above — usually considered within the normal range, though other findings matter
- 70–79% — mild reduction
- 60–69% — moderate reduction
- 50–59% — moderately severe reduction
- Below 50% — severe reduction
These cutoffs are general guidance. Your doctor interprets the numbers alongside your symptoms, history, and other test results. A single number never tells the whole story.
The FEV1/FVC ratio is also important. A ratio below roughly 0.70 after a bronchodilator is a common threshold doctors use to identify airflow obstruction. But this threshold becomes less reliable in older adults, where the ratio naturally declines with age, and in younger people, where a higher cutoff may be more appropriate. This is one area where clinical judgment matters more than any single number.
Your doctor may also compare your current results to previous ones. A decline over time can be more meaningful than any single test.
What Other Lung Function Tests Exist?
Spirometry is the starting point, but it does not measure everything. Other tests give a fuller picture.
Lung volume measurement (plethysmography or gas dilution) measures total lung capacity, residual volume, and functional residual capacity. Spirometry cannot measure how much air stays in your lungs after you exhale as much as you can — that leftover air is called residual volume. Lung volume testing can. This matters for diagnosing restrictive diseases and distinguishing them from obstructive ones.
Diffusing capacity (DLCO) measures how well oxygen moves from your lungs into your bloodstream. It can be reduced in conditions that damage the lung’s air sacs or the blood vessels around them, such as emphysema or pulmonary fibrosis. A low DLCO does not tell you what is causing the problem, but it narrows the possibilities.
Pulse oximetry and arterial blood gas tests measure oxygen levels in your blood. They are not lung capacity tests in the strict sense, but they often go together with lung function testing when doctors need to know whether your lungs are getting enough oxygen into your blood.
Six-minute walk test measures how far you can walk in six minutes while your oxygen level and heart rate are monitored. It is a functional test rather than a lung capacity test, but it can show how lung disease affects your daily activity.
Not everyone needs all of these. Your doctor will choose based on your symptoms and what the initial spirometry shows.
What Are the Limitations of Lung Capacity Tests?
Lung capacity tests are useful, but they have real limits. They require your full effort, and results can vary from one test to another even in the same person. A difference of a few percentage points between tests may not mean anything.
They also cannot tell you the cause of a problem on their own. A low FEV1 could come from asthma, COPD, or something else entirely. The test shows a pattern; your doctor connects it to your history and other findings to reach a diagnosis.
Reference values are based on population averages, and they do not fit everyone equally well. This is a known issue in pulmonary medicine, especially for people of different ethnic backgrounds. Some organizations have moved toward race-neutral reference equations, but this is still an area of active discussion.
Spirometry also cannot measure lung volume or diffusing capacity, which is why additional tests are sometimes needed. And it may miss early or mild disease — a normal spirometry result does not always mean your lungs are completely healthy.
Frequently Asked Questions
What is a lung capacity test used for?
It is used to measure how much air your lungs can hold and how well you can move air in and out. Doctors use it to diagnose conditions like asthma and COPD, assess severity, and track how treatment is working.
Does a lung capacity test hurt?
No, it does not hurt. You may feel lightheaded or short of breath during the test because you are breathing deeply and forcefully, but this passes within a minute or two.
How long does a lung capacity test take?
The test itself usually takes about 10 to 15 minutes. You will repeat the breathing maneuver at least three times to get a reliable result.
Can you eat before a lung capacity test?
A light meal is usually fine, but a heavy meal right before the test can make it harder to take deep breaths. Your doctor may give you specific instructions based on your situation.
