

Weaning off pumping is a physical transition, not just a scheduling change. Your breasts have been producing milk on a demand-driven feedback loop, and when you suddenly remove that demand, the milk that is already there has nowhere to go. That backup is what creates the pressure, clogged ducts, and infection risk people worry about. The way to avoid mastitis is to reduce pumping gradually, remove only enough milk to relieve pressure rather than empty the breast, and watch closely for signs of inflammation or infection in the first days of each reduction.
Why Does Weaning Off Pumping Cause Mastitis?
Mastitis is inflammation of breast tissue, and it most often happens when milk is not removed effectively or often enough. During weaning, that is exactly the situation you are creating on purpose.
Here is the mechanism. Milk production works on supply and demand. When milk is removed, the breast gets a signal to make more. When milk sits in the breast, production slows. That is the system you are trying to use to your advantage. The problem is the transition window. If you drop from several pumping sessions to none in a short time, milk stays in the ducts, pressure builds, and the tissue around those ducts becomes inflamed.
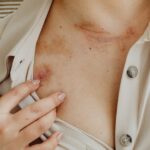
Inflammation alone can cause pain, redness, and swelling. That is sometimes called a clogged duct or inflammatory mastitis. If bacteria enter through a cracked nipple or multiply in milk that is sitting stagnant, that inflammation can progress to an infection. This is why the standard advice is to slow down rather than stop.
One clarification that matters: mastitis is not caused by cold, by stress, or by “bad milk.” Those are old ideas. The evidence points to milk stasis and, in infectious cases, bacteria — most commonly Staphylococcus aureus — as the drivers.
How Fast Should You Reduce Pumping Sessions?
Slower is safer. There is no single schedule that fits everyone, because how fast you can reduce depends on your supply, how long you have been pumping, and how your breasts respond.
The general approach clinicians use is to stretch the time between sessions and shorten each session, one change at a time. A common pattern is to drop one session every few days, then wait to see how your breasts respond before dropping the next. Some people can move faster. Others need to go slower, especially if they have a history of clogged ducts or mastitis.
Watch for these signals that you are moving too fast:
- Breasts feel hard, swollen, or painful between sessions
- You feel a firm, tender lump that does not ease after pumping
- Redness or warmth in one area of the breast
- Low-grade fever or body aches
If any of these appear, slow down. Do not push through. A single extra session to relieve pressure is not a failure — it is how you protect yourself from a bigger setback.
How Do You Relieve Pressure Without Emptying the Breast?
This is the part most people get wrong. When you are weaning, the goal of each session is relief, not drainage.
If you fully empty the breast every time you pump, you are sending the same “make more milk” signal you have been sending all along. That keeps your supply up and makes weaning harder. Instead, pump or hand-express just until the sharp pressure eases. Stop while the breast still feels somewhat full. That leftover milk is what tells your body to slow production.
Practical steps that help:
- Pump for a shorter time than usual, not to empty
- Use hand expression for comfort instead of a full pump session
- Apply a cool compress after pumping to reduce swelling
- Wear a supportive bra that is not tight enough to compress the ducts
- Avoid prolonged heat on the breast, which can increase swelling and blood flow
Gentle massage toward the nipple during expression can help move milk that is sitting in a duct. Firm, aggressive massage is not helpful and can increase inflammation.




What Are the Warning Signs You Should Not Ignore?
Most weaning discomfort is manageable. Some symptoms mean you need medical care.
Contact a doctor promptly if you have:
- Fever of 100.4°F (38°C) or higher
- Flu-like symptoms — chills, aching, feeling generally unwell
- A red, hot, swollen area that is getting worse rather than better
- Breast pain that is severe or not improving within a day or two
- Fluid or pus coming from the nipple
Infectious mastitis generally needs antibiotics, and delaying treatment raises the risk of a breast abscess, which may need to be drained. This is not a situation to wait out. If you are unsure whether what you have is inflammatory or infectious, call your doctor. That distinction is not always obvious, and it is not something to self-diagnose.
If you are breastfeeding and weaning, the same guidance applies. Weaning from nursing and weaning from pumping share the same physiology.
How Long Does It Take to Stop Pumping Completely?
There is no standard timeline. It varies widely from person to person, and that variation is normal.
Some people taper over a couple of weeks. Others take a month or longer, especially if they had a high supply or have pumped for a long time. The pace is set by your body’s response, not by a calendar.
What matters more than speed is consistency. Dropping sessions in a steady, gradual way gives your milk supply time to down-regulate without creating the stasis that leads to mastitis. Trying to rush the process is the most common reason weaning goes badly.
Once you have stopped entirely, some milk production may continue for a while. This is normal. It usually resolves on its own. If you notice ongoing leakage, a persistent lump, or continued pain weeks after stopping, that is worth a conversation with your doctor.
What If You Get a Clogged Duct While Weaning?
A clogged duct feels like a tender, firm spot in the breast. It is a warning sign that milk is not moving well, and it can progress to mastitis if it is not addressed.
What tends to help:
- Express milk gently from the affected area — enough to soften it, not to empty
- Apply a cool compress to reduce swelling
- Continue your taper but do not drop sessions faster than planned
- Drink fluids and rest
What does not help: aggressive massage, deep heat, or trying to “pump it out” forcefully. Those approaches can worsen inflammation.
If the lump does not ease within a day or two, or if you develop fever or flu-like symptoms, see a doctor. A clogged duct that turns into an infection needs treatment.
Is There Anything That Makes Weaning Riskier?
Some situations raise the chance of complications, and it helps to know if any apply to you.
People with a history of mastitis, a previous breast abscess, or chronic clogged ducts tend to need a slower taper. The same is true if you have a very high milk supply, since your body has more milk to down-regulate.
Structural factors such as a nipple that does not drain well, or a prior breast surgery, can also affect how smoothly weaning goes. If any of these apply, it is reasonable to check in with a doctor or a lactation consultant before you start reducing sessions, rather than after a problem appears.
There is no evidence that any supplement, tea, or food reliably stops milk production. Some traditional remedies are widely used, but clinical evidence for them is limited. If you are considering one, talk to your doctor first, especially if you take any medication.
Frequently Asked Questions
How do I stop pumping without getting mastitis?
Reduce sessions gradually, one change at a time, and pump only until pressure eases rather than emptying the breast. This gives your supply time to slow down without creating the milk backup that leads to mastitis.
How long should I wait between dropping pumping sessions?
There is no fixed schedule, but spacing drops out by several days lets you see how your breasts respond before making the next change. If you feel hard, swollen, or painful, slow down.
Can I just stop pumping cold turkey?
Stopping suddenly raises the risk of clogged ducts and mastitis because milk stays in the breast with no outlet. A gradual taper is safer for most people.
When should I call a doctor about weaning symptoms?
Call if you have a fever of 100.4°F (38°C) or higher, flu-like symptoms, or a red, hot, swollen area that is getting worse. Infectious mastitis generally needs antibiotics, and delaying treatment raises the risk of an abscess.
