
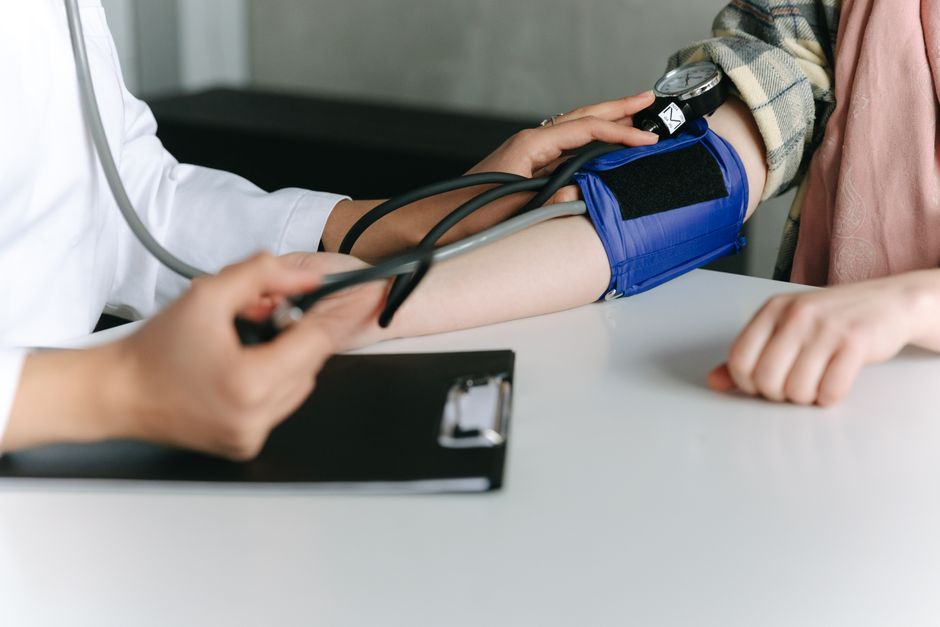
Measuring blood pressure by auscultation means listening to the sounds blood makes as it moves through an artery while a cuff briefly squeezes that artery shut. You wrap a cuff around the upper arm, inflate it above the point where blood flow stops, then release the pressure slowly while holding a stethoscope over the brachial artery at the inside of the elbow. The first tapping sound you hear is the systolic pressure, and the point where the sounds disappear is the diastolic pressure.
This is the method behind every manual blood pressure reading, and it is still the reference standard that automated monitors are checked against. It takes practice, but the steps are not complicated once you understand what you are listening for.
What Equipment Do You Need to Measure Blood Pressure by Auscultation?
You need three things: a blood pressure cuff with a pressure gauge, a stethoscope, and a way to support the arm at heart level. The cuff and gauge together are called a sphygmomanometer.
Cuff size matters more than most people realize. The inflatable bladder inside the cuff should wrap around about 80 percent of the arm’s circumference, and the cuff itself should cover roughly two-thirds of the distance between the shoulder and the elbow. A cuff that is too small will read artificially high. One that is too large can read artificially low. Most adults need a standard adult cuff, but people with larger arms often need a large adult cuff, and children need pediatric sizes.
For the stethoscope, a standard acoustic model with a bell and a diaphragm works well. The bell is traditionally used for blood pressure because it picks up low-frequency sounds. Many clinicians use the diaphragm instead and get good results, so either is acceptable in practice.
Aneroid gauges (the dial type) need to be checked for accuracy. They can drift out of calibration if dropped. Mercury gauges were long considered the gold standard but have largely been phased out for safety and environmental reasons. Digital gauges built into automated devices are common now, but the auscultation method specifically refers to listening with a stethoscope.
How Do You Position the Patient and the Arm?
Position affects the reading as much as technique does. Get this part right before you inflate anything.
The person should sit quietly for at least five minutes before the measurement. During that time, no caffeine, no smoking, and no exercise. These all push blood pressure up temporarily and can make a normal reading look high.
Have them sit in a chair with their back supported and both feet flat on the floor. Do not let them cross their legs. The arm should be bare — a sleeve rolled up can act like a tourniquet and distort the reading, so remove the clothing from the arm rather than rolling it tightly.
Rest the arm on a table so the cuff sits at roughly the level of the heart. If the arm hangs below heart level, gravity adds pressure and the reading runs high. If it is held above heart level, the reading runs low. This is one of the most common sources of error in home and clinic measurements alike.
Wrap the cuff snugly around the upper arm with the bottom edge about one inch above the bend of the elbow. The center of the bladder should sit over the brachial artery, which runs down the inner side of the arm.
Where Do You Place the Stethoscope?
Place the stethoscope over the brachial artery, just above the crease of the elbow on the inner side of the arm.
To find the artery, you can first locate the pulse by pressing two fingers into that area. Once you feel it, that is where the stethoscope head goes. Press the stethoscope lightly against the skin — firm enough to make a seal, but not so hard that you press the artery shut. Pressing too hard creates its own noise and can silence the sounds you are trying to hear.
Make sure the earpieces point forward into your ears. Sounds are faint, and a poor seal in the ears is an easy way to miss them.
What Are the Korotkoff Sounds and What Do They Mean?
The sounds you hear through the stethoscope are called Korotkoff sounds, named after the Russian physician who described them. They occur because the cuff is partially blocking the artery, and blood squirting through the narrowed opening creates turbulence you can hear.
There are five phases, but only two matter for a standard reading:
- Phase 1: The first clear tapping sound appears. This is the systolic pressure — the top number.
- Phase 2: Sounds soften and may have a swishing quality.
- Phase 3: Sounds become crisper and louder again.
- Phase 4: Sounds become muffled and dull.
- Phase 5: Sounds disappear completely. This is the diastolic pressure — the bottom number.
In most adults, phase 5 is used for the diastolic reading. In some situations — pregnancy, children, and certain conditions where sounds never fully disappear — clinicians may use phase 4 instead. That is a judgment call best left to a trained professional.
What Is the Step-by-Step Procedure?
Here is the sequence from start to finish.
- Have the person sit quietly for five minutes with their back supported and feet flat on the floor.
- Position the bare arm on a table at heart level, palm facing up.
- Wrap the correctly sized cuff around the upper arm, bottom edge about one inch above the elbow crease.
- Find the brachial pulse with your fingers, then place the stethoscope over that spot.
- Close the valve on the bulb and inflate the cuff to about 30 mmHg above the point where you last heard a pulse sound. If you are unsure, inflating to around 180 to 200 mmHg is a common starting point for adults, then adjusting as needed.
- Release the valve slowly so the pressure drops at about 2 to 3 mmHg per second. Faster than that and you will miss the exact pressures. Slower can cause venous congestion and falsely elevated readings.
- Note the pressure on the gauge when you hear the first tapping sound — that is systolic.
- Keep listening as the sounds change and fade.
- Note the pressure when the sounds disappear — that is diastolic.
- Let the cuff deflate fully. Wait at least one minute before repeating. Take two readings and average them if you need a more reliable number.
The 2 to 3 mmHg per second deflation rate is not a rough guideline. It comes from established clinical standards, and going faster is one of the most common reasons for inaccurate readings.
What Causes Inaccurate Readings?
Errors in auscultation usually come from a handful of predictable sources.
Wrong cuff size is the most frequent problem. Too small reads high, too large reads low.
Arm position matters. An arm below heart level adds pressure from gravity and inflates the number.
Deflating too fast causes you to miss the true systolic and diastolic points. This is especially common in busy clinics.
Talking during the measurement raises blood pressure in both the person being measured and, if you are the one talking, distracts you from listening.
White coat effect is real. Some people run higher in a clinical setting simply because they are anxious. Home readings often look different for this reason.
Background noise makes the Korotkoff sounds hard to hear. A quiet room is not a luxury — it is part of the technique.
Hearing loss in the person taking the reading is an underrecognized issue. If you cannot hear the sounds clearly, you cannot measure accurately. This is one reason automated devices have become so common.
How Does Auscultation Compare to Automated Monitors?
Automated oscillometric monitors — the kind that inflate on their own and show a digital number — use a different principle. They detect the tiny pressure oscillations in the cuff as blood pulses through the artery, rather than listening to sound.
For most routine measurements, automated devices are accurate and easier to use correctly. They remove the human variables of hearing, reaction time, and deflation speed. Many clinical guidelines now favor validated automated devices for routine office readings for exactly these reasons.
Auscultation remains important in specific situations: when automated readings are unreliable, when the heart rhythm is irregular, when you need to confirm an abnormal reading, and in settings where automated equipment is not available. It is also the method against which automated devices are validated, so understanding it helps you understand what your monitor is actually doing.
One non-obvious point: an automated monitor that has never been validated against a reference standard may give you a consistent number that is consistently wrong. Validation matters more than brand or price.
Can You Measure Blood Pressure by Auscultation at Home?
Yes, but it takes practice and a decent stethoscope. Many people find it harder than expected, especially hearing the diastolic point clearly.
If you want to try, practice alongside a validated automated monitor first and compare readings. If your auscultation numbers consistently differ from the automated ones by more than a small margin, the issue is usually technique or hearing rather than the device.
For most home users, a validated automated upper-arm monitor is the more practical choice. Wrist and finger monitors are generally less reliable. Whatever you use, bring the device to a clinical visit so it can be checked against a reference measurement.
Frequently Asked Questions
What is the correct deflation rate for manual blood pressure?
The cuff should be deflated at about 2 to 3 mmHg per second. Going faster than this is a common cause of inaccurate readings because you can miss the exact points where sounds start and stop.
Which Korotkoff sound is the diastolic pressure?
In most adults, the diastolic pressure is phase 5 — the point where sounds disappear completely. In pregnancy, children, and certain other situations, clinicians may use phase 4, the muffled point, instead.
Why does my manual blood pressure reading differ from my monitor?
Differences usually come from cuff size, arm position, deflation speed, or hearing. An arm below heart level reads high, and deflating too quickly causes errors in both numbers.
Can I measure my own blood pressure by auscultation?
It is possible but difficult, because inflating the cuff and listening at the same time takes coordination. A validated automated upper-arm monitor is more practical for most people measuring at home.
