
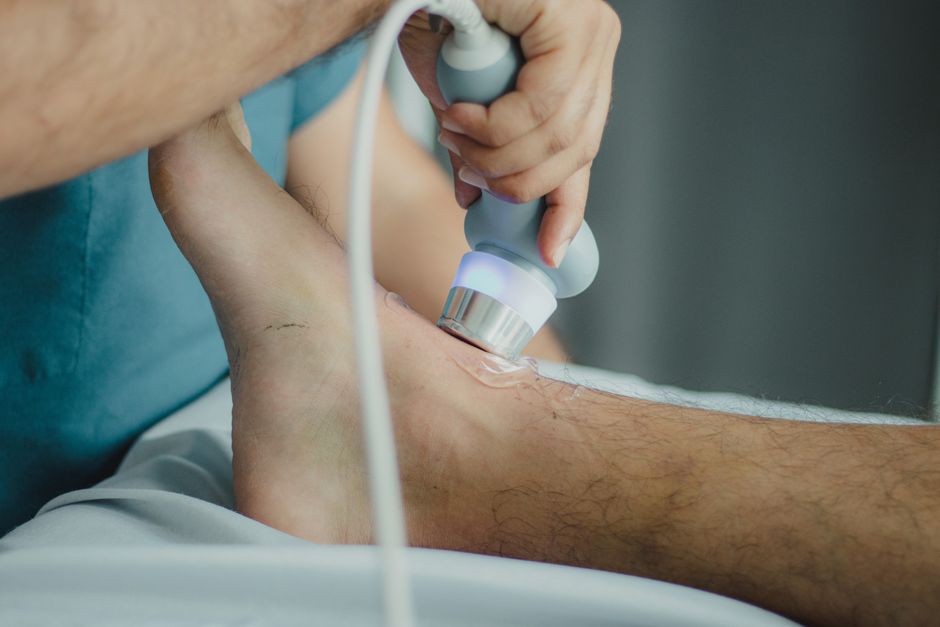
Peripheral neuropathy is damage to the nerves outside your brain and spinal cord, and it usually cannot be reversed once it has developed. The most effective steps you can take are to treat the underlying cause, protect your feet from injury, manage pain with treatments that have real evidence behind them, and stay physically active. For many people the goal is not a cure but slower progression, less pain, and a lower risk of falls and wounds.
If you have been told you have neuropathy, you have probably already noticed that the advice online ranges from sensible to strange. This article sticks to what is actually supported: what helps, what does not, and where the honest limits are.
What Is Peripheral Neuropathy and What Causes It?
Peripheral neuropathy means the nerves carrying signals between your body and your spinal cord are damaged or not working properly. Those nerves handle sensation, muscle control, and automatic functions like blood pressure and digestion.
Damage usually starts in the longest nerves, which is why symptoms most often begin in the toes and feet and move upward over time. A common pattern is numbness, tingling, burning, or a feeling like you are wearing socks when you are not. Some people get sharp, stabbing pain or extreme sensitivity to light touch. Others lose balance because they cannot feel the floor clearly.
The causes are many, and identifying yours matters more than any single remedy.
- Diabetes is the most common cause in the United States. High blood sugar over years damages nerves directly and through reduced blood flow.
- Vitamin B12 deficiency can cause neuropathy that sometimes improves with replacement, which is why testing matters.
- Alcohol use disorder damages nerves through direct toxicity and poor nutrition.
- Kidney disease, thyroid disease, and liver disease can all affect nerves.
- Chemotherapy causes a painful neuropathy in some patients that often eases after treatment ends, though not always completely.
- Inherited conditions such as Charcot-Marie-Tooth disease.
- Unknown cause — a substantial share of cases are never fully explained, which is called idiopathic neuropathy.
One point that surprises many people: about a third of cases are not caused by diabetes. If your doctor has not looked for other causes, that is worth raising. A basic workup usually includes blood glucose testing, vitamin B12, thyroid function, kidney function, and sometimes protein electrophoresis to look for unusual antibodies.
Can Peripheral Neuropathy Be Cured?
For most causes, no. Nerve tissue in the peripheral nervous system can regrow, but the regrowth is slow and often incomplete. This is why honesty matters here — no supplement, cream, or device has been shown to reverse established neuropathy.
There are important exceptions. If the cause is a vitamin deficiency that gets corrected, or a medication that gets stopped, or an underactive thyroid that gets treated, symptoms can improve or resolve. That is why finding the cause is not just good practice — it is sometimes the only path to meaningful recovery.
For diabetic neuropathy, the strongest evidence points to tight blood sugar control slowing progression. Research consistently shows that intensive glucose management reduces the incidence and progression of diabetic neuropathy, though it does not typically reverse damage already present.
What you can realistically aim for:
- Slower progression
- Less pain and better sleep
- Fewer falls and injuries
- Preserved independence
That may sound modest. In practice it is not. Preventing a foot ulcer or a serious fall changes lives.
How to Get Rid of Peripheral Neuropathy Pain: What Actually Works
Pain from neuropathy responds differently than most other pain. Standard over-the-counter pain relievers like ibuprofen and acetaminophen generally do not help much, because the problem is in the nerves themselves rather than in tissue injury. That is a genuinely useful thing to know before you spend months on drugs that were never likely to work.
Medications with the best evidence are in a few specific classes. Some antidepressants — particularly certain tricyclics and SNRIs — reduce nerve pain at doses lower than those used for depression. Some anti-seizure medications, including gabapentin and pregabalin, are also used, though their benefit varies and side effects like drowsiness and dizziness are common. A topical lidocaine patch or capsaicin cream helps some people, particularly with localized burning.
No clinical guidelines currently exist for choosing between these based on neuropathy type alone. In practice, doctors try one, assess response over several weeks, and adjust. What works for one person may not work for another, and combining medications is sometimes necessary.
Non-drug approaches with reasonable supporting evidence include:
- Regular aerobic exercise — walking, swimming, cycling. Some studies indicate exercise reduces neuropathic pain and improves nerve function, though results vary.
- Physical therapy for balance and strength, which reduces fall risk.
- Cognitive behavioral therapy for the distress that chronic pain creates. This does not remove the pain but changes how much it interferes with life.
- TENS units — the evidence is mixed. Some people find relief; trials have not shown consistent benefit.
Approaches with weak or absent evidence include most oral supplements marketed for nerve health, magnets, and many compounded creams. If a product promises to “rebuild” nerves, that claim is not supported by human trials.


Which Supplements and Vitamins Have Evidence?
Only one category has clear evidence: correcting a documented deficiency. If your B12 is low, replacing it can improve or resolve neuropathy. If it is normal, taking more does not help.
Beyond that, the picture is thin.
Alpha-lipoic acid has been studied for diabetic neuropathy, and results have been mixed. Some trials show modest pain reduction; others show no difference from placebo. It is generally well tolerated but can lower blood sugar, which matters if you take diabetes medication.
Benfotiamine, a form of vitamin B1, has some small studies suggesting benefit in diabetic neuropathy. The trials are not large or consistent enough to call this established.
Vitamin B6 is a case where more is not better. High-dose B6 over time can actually cause neuropathy. This is a real risk with megadose supplements, and it is underrecognized.
No clinical guidelines currently recommend routine supplementation for neuropathy in people without a documented deficiency. If you want to try something, discuss it with your doctor first — especially anything that affects blood sugar or interacts with medications.
Daily Habits That Protect Your Feet and Nerves
Because neuropathy reduces sensation, injuries can go unnoticed until they become serious. Foot care is not a minor detail — it is central to staying mobile and avoiding amputation, which is a real risk when wounds are missed.
What helps:
- Inspect your feet daily. Use a mirror or ask someone to check the bottoms. Look for cuts, blisters, redness, or swelling.
- Wash and dry carefully, especially between the toes.
- Moisturize but not between the toes, where moisture encourages fungal growth.
- Trim nails straight across and file edges. Consider a podiatrist if your vision or flexibility makes this hard.
- Never go barefoot, even indoors. A small object can cause a wound you will not feel.
- Wear shoes that fit well and check inside them before putting them on.
- Stop smoking. Smoking reduces blood flow to the feet, which worsens healing.
- Limit alcohol. It is directly toxic to nerves and worsens deficiency risk.
For blood sugar, the general target for most adults with diabetes is an A1C below 7%, though your doctor may set a different goal based on your age, other conditions, and hypoglycemia risk. Tight control is the single most evidence-supported step for slowing diabetic neuropathy.
When to See a Doctor and What to Ask
See a doctor promptly if you have new numbness, burning, weakness, or balance problems. Early evaluation gives the best chance of finding a treatable cause.
Seek urgent care if you notice a foot wound you cannot feel, spreading redness, fever, or sudden weakness. These are not wait-and-see situations.
Questions worth asking at your appointment:
- What is the likely cause of my neuropathy?
- Have we tested for vitamin B12 deficiency, thyroid problems, and kidney function?
- Are any of my current medications contributing?
- What are the risks and benefits of the treatment you are recommending?
- Should I see a neurologist or podiatrist?
A neurologist can confirm the diagnosis with nerve conduction studies or a skin biopsy if the picture is unclear. A podiatrist can help with foot protection and nail care. Physical therapy helps with balance and strength.
One clarification worth making: neuropathy is not a single disease. It is a symptom pattern with many causes, and the right approach depends entirely on which one you have. Anyone offering a universal fix is not giving you accurate information.
Frequently Asked Questions
Can peripheral neuropathy be reversed?
In most cases, no — established nerve damage does not fully reverse. It can improve when a treatable cause such as vitamin B12 deficiency or an offending medication is corrected.
What is the best treatment for peripheral neuropathy pain?
Certain antidepressants and anti-seizure medications have the strongest evidence for reducing nerve pain. The best choice varies by person, and response is often partial rather than complete.
Does exercise help peripheral neuropathy?
Some studies indicate regular aerobic exercise reduces neuropathic pain and improves nerve function, though results vary. It also improves balance and reduces fall risk, which matters regardless of pain.
What vitamin is good for nerve repair?
Vitamin B12 can improve neuropathy when a deficiency is documented. If your B12 level is normal, taking more has not been shown to help, and high-dose vitamin B6 can actually cause nerve damage.
