
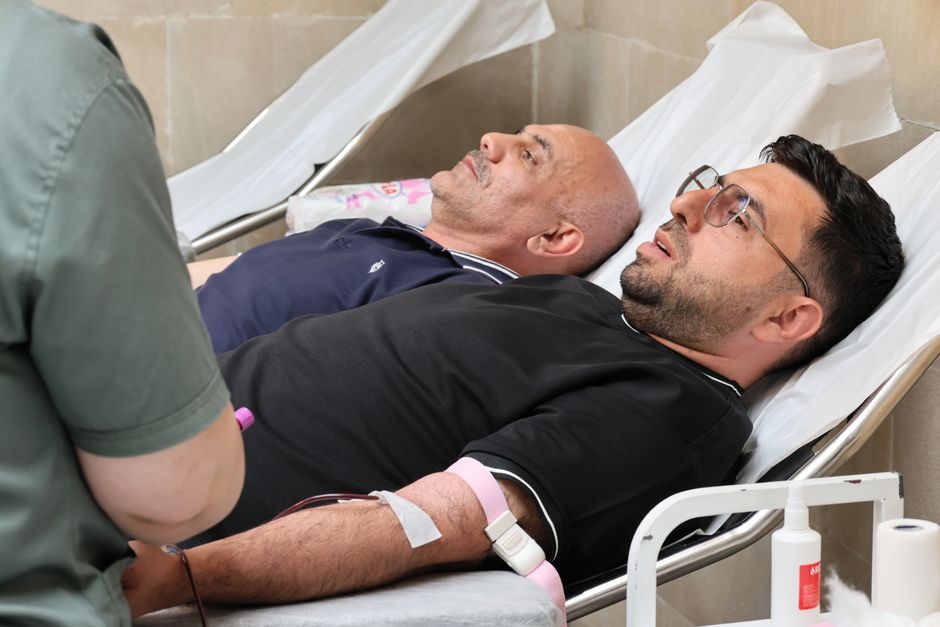
There is no single schedule that fits everyone. For most healthy adults with no symptoms and no chronic conditions, routine blood work every one to three years is a reasonable range. People with diabetes, heart disease, kidney disease, or thyroid disorders often need testing every three to six months, and sometimes more often. The right answer depends on your age, your health history, and what your doctor is actually looking for.
How Often Should You Get Blood Work Done?
For a healthy adult under 50 with no symptoms and no ongoing medical conditions, most clinicians order routine blood work every one to three years. That range is a common clinical practice, not a fixed rule handed down by a single authority. Different medical organizations and primary care systems set their own intervals.
Once you turn 50, many clinicians move toward annual or every-other-year testing. This is partly because the risk of several conditions rises with age. It is also partly habit — annual physicals have long included blood work, and that pattern has been hard to break even where the evidence for yearly testing in healthy people is thin.
If you have a diagnosed condition, the picture changes. Diabetes, high cholesterol, thyroid disease, kidney disease, and blood clotting disorders all require regular monitoring. In those cases, testing every three to six months is typical. Some medications, like blood thinners or thyroid replacement, need lab checks even more often when a dose is being adjusted.
The key point: there is no universal number. Anyone who tells you every adult needs a full panel every year is describing a habit, not a guideline.
What Does Routine Blood Work Actually Check?
A standard panel usually includes a complete blood count (CBC) and a basic metabolic panel (BMP) or comprehensive metabolic panel (CMP). These are the workhorses of primary care.
The CBC measures red blood cells, white blood cells, and platelets. It can flag anemia, infection, and some bleeding or clotting problems. The metabolic panel checks electrolytes, kidney function, liver enzymes, and blood glucose. A lipid panel — cholesterol and triglycerides — is often added.
Reference ranges matter here. A normal fasting glucose is 70–99 mg/dL. Normal blood pressure is 120/80. These numbers are established and consistent across clinical labs. What is not consistent is how different labs set their reference ranges for other tests. One lab’s “normal” can differ slightly from another’s.
Some tests get added based on who you are. A thyroid panel is common if you have fatigue or weight changes. An A1C test, which reflects average blood sugar over roughly the past two to three months, is often used to screen for prediabetes and diabetes. Vitamin D and B12 checks are frequently ordered, though routine screening of these in people without symptoms is debated.
Does Everyone Need the Same Tests?
No. Age, sex, family history, and existing conditions all shape what gets ordered.
Men and women share most routine tests, but some differ. Women may have hormone panels or pregnancy-related testing. Men may have prostate-specific antigen (PSA) discussions, though routine PSA screening is genuinely debated and not recommended universally.
Family history is a major factor. If a parent had early heart disease, your lipid testing may start younger and happen more often. If diabetes runs in your family, glucose screening may be prioritized.
Age changes things too. Cholesterol screening is generally recommended starting in the 20s for most adults. Colorectal cancer screening typically begins around age 45. These are screening recommendations, not blood tests alone, but they influence what labs get ordered alongside them.
Here is a non-obvious point: more testing is not automatically better. False positives are real. A slightly abnormal result can trigger follow-up tests, anxiety, and procedures that turn out to be unnecessary. This is why routine screening in low-risk people is not always a clear win.



How Often Should You Get Blood Work Done If You Have a Chronic Condition?
If you have diabetes, testing is frequent and structured. An A1C test is typically done every three to six months, depending on how well blood sugar is controlled. Kidney function and cholesterol are checked at least yearly.
For thyroid disease, TSH levels are usually checked six to eight weeks after any dose change, then less often once stable. For people on blood thinners like warfarin, INR testing can be needed as often as weekly at first, then monthly once stable.
Kidney disease and heart disease both call for regular monitoring of electrolytes, kidney function, and lipids. The exact interval depends on severity and medication. Your doctor sets this, not a general rule.
The pattern: the more active the condition and the more medications involved, the more often you get tested.
What About Testing When You Have Symptoms?
This is different from routine screening. If you have symptoms — unexplained fatigue, weight loss, fever, persistent pain, unusual bruising — blood work is ordered to investigate, not on a schedule. The timing depends entirely on what is being evaluated.
Screening is testing people who feel fine to catch disease early. Diagnostic testing is investigating a specific problem. These serve different purposes and follow different logic.
Mixing them up causes confusion. A normal routine panel does not rule out every condition. It checks specific things. If you have symptoms, tell your doctor, because the right test depends on the symptom.
Are There Downsides to Testing Too Often?
Yes, and they are underdiscussed. Frequent testing in healthy people can lead to incidental findings — small abnormalities that would never have caused a problem but now require follow-up.
This can mean more tests, more specialist visits, and in some cases procedures that carry their own risks. It can also cause real anxiety. Research on overdiagnosis suggests that finding something early is not always the same as helping someone live longer or better.
There is also cost. Insurance may not cover tests that are not medically indicated, and repeat testing adds up.
None of this means testing is bad. It means the frequency should match your actual risk, not a fixed calendar.
How Do You Know What Schedule Is Right for You?
Ask your doctor three questions: What are you testing for? What would change based on the result? When should we test again?
The answers should be specific. If a test is ordered “just to check,” that is worth questioning. Good testing has a purpose.
For most healthy adults, a reasonable starting point is a baseline panel in your 20s or 30s, then repeat testing every one to three years depending on results and risk factors. After 50, or with any chronic condition, the interval usually shortens.
Your personal schedule is a conversation, not a formula. Bring your questions. The best plan is one you understand and your doctor can justify.
Frequently Asked Questions
How often should a healthy adult get blood work done?
Most healthy adults without symptoms or chronic conditions can get routine blood work every one to three years. People over 50 or with risk factors often test more frequently.
Is annual blood work necessary?
Not for everyone. Annual testing is common in clinical practice, but for healthy adults with normal results, the evidence for yearly testing is limited. Frequency should match your individual risk.
How often should diabetics get blood work?
People with diabetes typically check A1C every three to six months, depending on control. Kidney function and cholesterol are usually checked at least once a year.
Can you get blood work done too often?
Yes. Frequent testing in healthy people can lead to incidental findings, unnecessary follow-up, anxiety, and added cost. Testing should have a clear purpose.
