
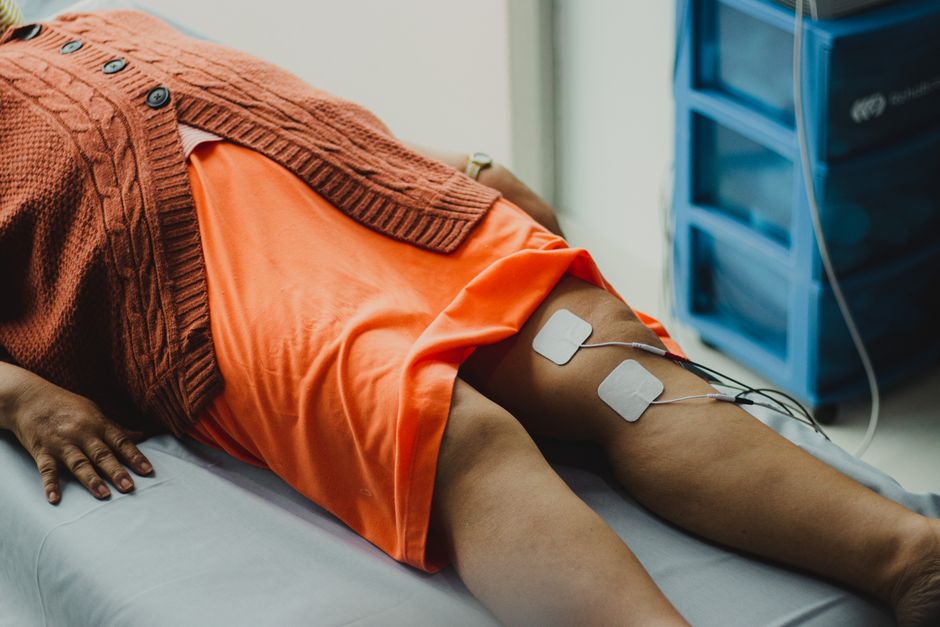
Nerve pain is stubborn. It often doesn’t respond well to standard painkillers, and it can linger for months or years. That’s why so many people with neuropathy, sciatica, or post-shingles pain end up looking at a TENS unit. The short answer: a TENS unit can help with nerve pain for some people, but the evidence is mixed and the benefit is usually modest. It works better as one part of a broader pain plan than as a standalone fix. It is not a cure, and it does not repair damaged nerves.
What Is a TENS Unit and How Does It Work?
TENS stands for transcutaneous electrical nerve stimulation. A small device sends low-voltage electrical pulses through electrodes placed on your skin. You feel a tingling or buzzing sensation. The intensity is adjustable, and most sessions run for a set period before the device shuts off.
The leading theory is called the gate control theory of pain. The idea is that the electrical signals from the TENS unit travel along large nerve fibers and, in effect, crowd out some of the pain signals traveling along smaller fibers at the spinal cord level. This is a well-established concept in pain physiology.
A second proposed mechanism involves the release of endorphins, the body’s natural pain-relieving chemicals. Some studies support this, but it is less firmly established than the gate control explanation.
Here is the part that matters for nerve pain specifically. TENS works on the nervous system’s signaling. It does not treat the underlying cause of nerve damage. If a nerve is compressed or damaged by diabetes, the electrical pulses do not repair it. What TENS may do is change how much of that pain signal reaches your brain.
Does a TENS Unit Help with Nerve Pain?
The evidence is mixed, and that is the honest position. Some people with nerve pain get meaningful relief. Others get little or none. Research has not reliably predicted who will respond.
What the research generally shows is that TENS produces modest pain reduction in some patients with neuropathic pain, but results across studies vary widely. Part of the problem is that studies use different devices, different settings, different electrode placements, and different definitions of success. This makes it hard to draw firm conclusions about how well it works on average.
Clinical guidelines reflect this uncertainty. Some guidelines list TENS as a reasonable option to try, often alongside medication, while noting the evidence is limited. Others are more cautious. The general clinical direction is that TENS is worth a trial in some patients because it is low-risk, but it should not replace treatments with stronger evidence.
There is an important nuance here. How TENS is used matters a great deal. The frequency and intensity settings, where the electrodes go, and how long each session lasts all affect results. A poorly placed or weakly set unit is unlikely to do much. Some research suggests that higher-frequency settings are more commonly used for nerve pain, but the optimal settings are not clearly established and vary by individual.
What Does the Evidence Actually Say About TENS and Neuropathy?
Neuropathic pain — pain caused by damage or dysfunction in the nervous system — is the category most relevant to nerve pain. It includes diabetic neuropathy, postherpetic neuralgia after shingles, and certain types of nerve injury.
Some studies suggest TENS can reduce pain intensity in people with painful diabetic neuropathy, but the trials are generally small and the results are not consistent. Similar patterns appear for postherpetic neuralgia. A few studies report benefit; others find no clear difference from a placebo device.
That placebo point deserves attention. TENS is hard to study in a blinded way because the person using it can feel whether it is on. This makes it difficult to separate real effect from expectation. Researchers have tried sham devices that deliver minimal current, but the comparison is imperfect.
What does seem clearer is safety. TENS has a good safety profile when used correctly. Serious adverse events are rare. The most common issues are skin irritation under the electrodes and mild discomfort if the intensity is set too high. That favorable safety profile is a large part of why clinicians are often willing to suggest a trial even when they are uncertain about benefit.
Who Should Not Use a TENS Unit?
TENS is not appropriate for everyone. Certain conditions make it unsafe or require medical clearance first.
- People with a pacemaker or implanted electrical device should not use TENS without asking their doctor. The current can interfere with these devices.
- Do not place electrodes over the front of the neck, over the head, across the chest, or over the eyes. These areas carry risks including effects on the heart and airways.
- Avoid using TENS over broken skin, areas of infection, or areas with poor sensation where you might not feel a burn or irritation.
- People who are pregnant should talk to their doctor before using TENS. No clinical guidelines currently establish its safety in pregnancy, so this needs individual medical advice.
- People with epilepsy or certain heart conditions should check with a clinician first.
Reduced sensation deserves extra emphasis for people with neuropathy. If you cannot feel your feet well, you may not notice skin irritation or a burn developing under an electrode. Check your skin after each session.
How Do You Use a TENS Unit for Nerve Pain Safely?
Start with guidance from a clinician or a physical therapist who can show you where to place the electrodes and what settings to try. Placement depends on where your pain is and which nerve is involved.
General principles that apply to most users:
- Place electrodes on clean, dry skin. Follow the device instructions for pad placement and replacement.
- Start at a low intensity and increase slowly until you feel a comfortable tingling, not pain.
- Keep sessions to the time recommended in your device’s instructions or by your clinician.
- Stop if you feel skin irritation, a burning sensation, or any discomfort that concerns you.
- Do not use the unit while driving or operating machinery.
- Keep the device away from water and follow all manufacturer warnings.
Give it a fair trial but set a limit. Some clinicians suggest trying TENS for a few weeks and stopping if there is no clear benefit. If it is not helping after a reasonable trial, it is reasonable to stop rather than keep using it out of habit.
How Does TENS Compare to Other Nerve Pain Treatments?
TENS is one option among several, and it is generally considered a complementary approach rather than a first-line treatment.
| Approach | Evidence strength | Typical role |
|---|---|---|
| Medications (certain antidepressants, anticonvulsants) | Stronger evidence base for neuropathic pain | Often first-line, prescribed by a clinician |
| TENS | Mixed and limited | Add-on trial; low risk |
| Physical therapy and exercise | Moderate evidence for some pain types | Part of a broader plan |
| Psychological approaches (pain education, CBT) | Moderate evidence | Helps with coping and pain perception |
This is not a ranking of what will work for you. Nerve pain varies enormously between people, and what helps one person may do nothing for another. The point is that TENS belongs in a plan, not in place of one.
If you are considering TENS, it is worth telling your clinician what else you are doing for pain. That way the whole picture stays coordinated.
What Should You Realistically Expect?
Expect modest relief at best, and expect it to vary. Some people notice a difference within a session. Others need several tries. Some get nothing at all.
TENS does not reverse nerve damage. It does not cure neuropathy. It does not fix a compressed nerve. If a company or seller promises a cure or guaranteed relief, that is a marketing claim, not a medical one. No study has confirmed that TENS reverses nerve damage.
What TENS may offer is a way to take the edge off pain for a period, which can make movement, sleep, or daily tasks a little easier. For some people that is worth having. For others it is not.
Your nerve pain is real, and it is frustrating in ways that people without it often do not understand. A tool that offers partial relief is not nothing. But it is also not a solution on its own. The most honest approach is to try it with clear expectations, keep your clinician informed, and lean on treatments with stronger evidence as the foundation of your plan.
Frequently Asked Questions
Does a TENS unit help with nerve pain?
It can help some people, but the evidence is mixed and relief is usually modest. It works best as one part of a broader pain plan, not as a standalone treatment.
How long does it take for a TENS unit to work?
Some people notice a change within a single session, while others need several tries to judge whether it helps. If there is no clear benefit after a few weeks of proper use, it is reasonable to stop.
Can a TENS unit cure nerve damage?
No. TENS changes how pain signals are perceived and does not repair damaged nerves or treat the underlying cause.
Is it safe to use a TENS unit every day?
For most people without implanted devices or other contraindications, daily use within the device’s instructions is generally considered low risk. Check with your clinician first, especially if you have a pacemaker, are pregnant, or have reduced skin sensation.
